Author: Medicat

texting students their medical appointments

Texting Students: Best Practices from Our Recent Webinar

When the University of Oregon moved an appointment reminder text from one hour out to three hours out, students started canceling in time for the clinic to refill those slots. A small change produced real, meaningful results.

That story was one of many shared during our recent webinar on texting best practices for campus clinics. Medicat’s Chief Evangelist Ruth Patten and CEO Lauren Pragoff were joined by Erika Boyers, Senior Assistant Director of Patient Services and Health Information Management at the University of Oregon.

Here’s a recap of what we covered, plus a free AI prompt guide to help you write better texts!

Why Texting Students Works

Students rarely put their phones down. Emails pile up and get buried, but a text shows up as a quick notification they can read and act on in seconds. And to be honest, that’s true for all of us, not just students.

Texting is already part of daily life. We get texts about flight changes, dentist appointments, and deliveries. Most of those texts include a link to take the next step. Campus clinics can use the same pattern for:

  • Appointment reminders for medical, counseling, and wellness visits
  • Immunization compliance nudges tied to campus deadlines
  • Event outreach, like mass flu and COVID vaccine clinics
  • Portal alerts when a secure message, lab result, or visit summary is ready

Keep It to 160 Characters

Medicat’s texting uses the “short code” model with a 160-character limit built into the system. Longer messages can split into several texts depending on the carrier. Spaces, numbers, and emojis all count, so every character needs to earn its place.

Use AI to Write Warmer, Clearer Texts

Fitting a helpful, friendly message into 160 characters is hard. That’s where AI can help. Lauren’s advice: the more specific your prompt, the better your result.

Tell the AI tool exactly what you need. Try asking it to:

  • Rewrite for warmth and clarity: “Your appt is at 10 am tomorrow. Don’t be late” can become something kinder.
  • Lower the reading level: Many news outlets write for easy reading. You should too.
  • Ease anxiety: Some visits feel stressful. The right words can help.
  • Skip internal or clinical slang: Ruth noted that campus shorthand can confuse new and international students.

Here’s a sample prompt from the session: “Rewrite this to sound warm and student-friendly. I work at a college health center, and I’m texting a college student. Keep it under 160 characters.”

Want more prompts like these? Download our free AI prompt guide and put them to work on your next round of texts.

Protect Privacy and Get Consent Right

In our live poll, managing opt-in and consent tied for the top challenge, along with making sure students read their texts. Both matter, and both start with trust.

Keep Health Details Out of the Text

A text should never reveal protected health information. Ruth reminded attendees that notifications can pop up on a lock screen where anyone might see them. Avoid:

  • The clinic’s full name or the provider’s name
  • Test results, even negative ones
  • Anything that hints at why the student is visiting

Instead, keep the text generic and link to the secure patient portal. At the University of Oregon, texts name the clinic type (like “immunization clinic”) but not the campus health center. Every text points students back to the portal for details.

Know Your School’s Opt-in Path

Start with your institution’s privacy and communication policy. If enrollment paperwork already allows texting and you manage immunization compliance in Medicat, you may be able to opt in the full student body. If not, a mass opt-in isn’t appropriate.

Ruth also shared that scheduling an appointment is generally treated as implied consent for that clinic to text the student. Check with your compliance team to confirm what applies on your campus. ACHA is a helpful resource for peer guidance on student health operations.

In Medicat, students can opt in or out through forms at each visit, a standing portal form, or a checkbox in their portal profile. They can also text STOP at any time to stop receiving text messages from your clinic.

How University of Oregon Reworked Reminder Timing

During the 2023-24 school year, Oregon sent appointment reminders 24 hours and one hour before each visit. Students weren’t canceling in time, and many arrived late. So, Erika’s team tested a new texting cadence. Here’s what they tried:

Reminder Why it works

24 hours before

Puts the visit on the student’s radar

3 hours before

Leaves time to cancel without a fee, plus the clinic can fill that slot

20 minutes before

Prompts students to make their way to the clinic and arrive early to check in

The result: more timely cancellations and more students arriving within the check-in window. In fact, Oregon saw a 170.5% increase in timely cancellations over three years after beginning this experiment!

Beyond appointment reminders

Oregon and other schools now use texting students for more than visits. Erika shared a few ideas that other campuses can borrow:

  • Referral recalls: A text nudge led more students to follow up with outside providers.
  • TB screening follow-ups: High-risk results trigger a text pointing to next steps in the student portal.
  • Student input: Erika works with her student health advisory board to test AI-drafted messages to increase survey completion rates.

One more tip: Oregon asked Medicat to protect the cell phone field, so nightly data feeds don’t overwrite the phone numbers staff update in person. Any Medicat customer can request this for particular fields through a support ticket.

Key Takeaways

Texting students works best when every message is short, private, and tied to one clear action. Timing matters too, as Oregon’s 24-hour, 3-hour, and 20-minute schedule shows.

Ready to start or sharpen your approach to texting students? Download our free AI prompt guide and request a live demo with our team.

Industry Articles

Recent Medicat News

Continue reading

ICD-10 and CPT Code Suggestions

AI-Powered ICD-10 and CPT Code Suggestions Save Precious Time

A 2024 study covered by the American Medical Association found that primary care physicians spend an average of 36 minutes in the EHR for every 30-minute visit. Much of that time goes to work that happens after the student leaves the room. Coding is one of the biggest parts of it.

Note Agent in MedicatOne offers ICD-10 and CPT code suggestions based on the visit itself. Providers spend less time searching through codes and more time with students.

Why Coding Is a Hidden Time Drain on Campus

College health clinics see waves of demand. Flu season, midterms, and final exams often result in demand peaks! After each visit, a provider still has to turn the conversation they had with the student into the right diagnosis and procedure codes.

That step may seem small, but it adds up over a full clinic day. It often means searching code sets, remembering the right level of detail, and checking that each code lands in the right part of the note. Some common pain points:

  • Time pressure: coding pushes documentation into lunch breaks or end of the day
  • Missed detail: under stress, it’s easy to capture the main complaint and leave out related diagnoses
  • Inconsistent data: when codes vary from provider to provider, patterns in student health visit types and demand are harder to see. For clinic directors and VPSAs, consistently coded data helps surface what students need and make the case for adding additional resources

How Note Agent Suggests ICD-10 and CPT Codes

Note Agent listens to the visit (with the student’s consent) and drafts the clinical note. Once the note is generated, the Coding tab fills with suggested codes. Both ICD-10 and CPT codes appear when they apply.

The provider stays in control the whole time. Nothing gets added to the chart until the provider chooses it. Here’s how the workflow goes:

  1. Review the suggestions: Look over the list of ICD-10 and CPT code suggestions in the Coding tab.
  2. Check what fits: Use the checkboxes to select codes matching your clinical judgment. You can also select all.
  3. Submit each set: Submit ICD-10 codes to the Diagnosis section and CPT codes to the Plan section. Each set is sent separately.
  4. Confirm the result: A pop-up tells you whether each code was added, or if it’s already in the note.

The process takes seconds, not minutes. It also cuts down on retyping since the codes go straight into the note’s building blocks.

See the Reasoning Behind Every Diagnosis Code

AI tools earn trust when you can see how they reach their answers. That’s why each ICD-10 suggestion includes a Show Evidence option. One click shows why Note Agent suggested each code based on the visit recording.

This helps providers make quick, confident decisions. If the evidence matches what happened in the visit, select the code. If it doesn’t, leave it unchecked and move on.

Example: A Midterm Headache, Coded in Minutes

Picture a student who comes to the health center with a persistent headache during midterms. They mention long nights of studying, poor sleep, extra caffeine intake, and hours spent consecutively on their laptop and phone. The provider focuses on the student, not on typing, while Note Agent records the conversation.

After the note is generated, the Coding tab suggests several options. These include tension-type headache (G44.209), stress due to work schedule (Z56.3), and sleep deprivation (Z72.820). A CPT code for an established patient office visit (99213) appears.

The provider clicks Show Evidence on the stress code. It notes that the headache is linked to stress during midterms, a work-related stressor for students. The provider selects the codes that fit, submits them, and reviews the final note before locking it.

The result is a fuller clinical picture. Sleep and stress factors that might have been skipped in a rush are now part of the record. That supports better follow-up care and clearer trend data across campus.

Counseling and wellness centers can benefit too. When a note type is set up with Note Agent, counselors can review suggested codes after a session instead of starting from scratch.

Key Takeaways

Coding shouldn’t be the reason your providers stay late. ICD-10 and CPT code suggestions in Note Agent turn the visit conversation into codes that providers can review, check, and submit in a few clicks. Show Evidence keeps every decision clear, and providers always make the final call.

To see how Note Agent could fit (and even improve) your clinic’s workflow, request a demo.

Industry Articles

Recent Medicat News

Continue reading

What Sets Medicat Apart

What Sets Medicat Apart

One Record, One EHR:

What Sets Medicat Apart

Most campus health leaders aren’t shopping for software; they’re trying to close gaps between systems never built to talk to each other. Medical over here, counseling over there, immunization compliance in a spreadsheet, accommodations in another.

Every disconnected system increases the risk of a student falling through the cracks. That’s the problem MedicatOne was built to solve. And here’s what makes it different from other college-specific EHRs.

It’s One Platform, Not Four Bolted Together

Medicat is one of the only college-focused EHRs that unifies medical, counseling, immunizations, and accessibility on a single student record. Not four products with an integration layer.

For a student, that means accessing care feels like walking through one door instead of four. For your staff, it means a counselor and a nurse practitioner are working with the same information when caring for a student.

Many vendors in the EHR space are point solutions that do one job well. Medicat is the consolidation play, and on a campus where student well-being touches every department, that consolidation is the whole game.

Modern Architecture, not a Legacy System

Medicat is cloud-hosted and web-based. There’s no fat client to install on every machine, no on-prem server for your IT team to babysit, no VPN gymnastics to see a record from the counseling center.

Campuses can’t afford the risk of running their sensitive student data on locally installed, client-backed, on-prem servers, an architecture designed for a different era of campus IT. If your current platform requires a local install and a server in a closet, you already know the upkeep (and security risk) that adds up over time.

Security That’s Actually Certified

Medicat is SOC 2, Type II certified. For an EHR provider, that’s not a nice-to-have; it’s essential. When you’re the one deciding where sensitive student data lives, “we take security seriously” means nothing if standardized audits and reviews don’t back up that claim.

Built for Students, Connected to the Clinic

Students live on their phones. MedicatOne gives them a full student portal where they can schedule appointments, complete forms, upload immunization records, and reach the clinic in one place.

Text message appointment reminders go out automatically, which is the simplest lever there is for cutting no-shows. Some EHRs leave students without a comprehensive student portal, so your front desk stays on the phone doing what the software should be doing.

Reporting and Benchmarking, Built In

MedicatOne has robust reporting built in, so you can pull utilization, immunization compliance, and diagnosis data without exporting to a spreadsheet and rebuilding each report by hand.

For counseling teams, MedicatOne supports the CCMH Standard Data Set, so your center’s outcomes line up with the national mental health benchmarking that CCMH members rely on. You can see how your students compare to peers across the country, using data you’re already collecting.

31+ Years of Supporting College Campuses

Medicat has spent 31+ years building for college health and counseling clinics. That focus shows up across our large, experienced support team, who know clinical workflows like the back of their hands.

The people behind our product are known names in the college health and counseling community. When you submit a support ticket or call our team,

In fact, nearly 25% of Medicat employees come from a background in clinical care or student health operations. They’ve run a front desk during immunization season, sat in on a counseling intake, and closed out end-of-year clinic reports in May. So, when you call our team, you’re talking to people who have done your job, not just supported the software that does it.

AI That Saves Real Hours, at a Price That Makes Sense

Medicat offers two AI-powered tools, both priced to be predictable and accessible. You pay a flat license fee, so you know the cost up front and can budget for it. Many AI products bill by usage instead, which means the price can climb significantly the more your team leans on them.

Here’s a bit more about each of our AI-powered tools:

  • ICM Agent automates immunization review. What used to take staff hours of manual document checking now happens in seconds. During compliance season, that’s the difference between a major backlog and a free Friday afternoon.
  • Note Agent handles clinical documentation and coding using the power of ambient listening technology. Get time back for your clinicians, at a fraction of the cost of traditional scribing technology.

Built for How Campuses Actually Buy

Not every clinic needs every bell and whistle on day one. Medicat’s pricing is modular, so a counseling or medical team can start where the need is most urgent, prove the ROI, and expand their use of Medicat’s tools as budget and services grow. You don’t have to buy everything to get immense value from MedicatOne.

Onboarding and Training Opportunities

You’re not expected to set up and learn a whole new EHR system alone. Onboarding is configured according to your institution’s needs and is led by one of our Customer Onboarding Specialists. Our vast library of educational content and regular training events help set you and your team up for success.

Plus, when you implement MedicatOne, you’re joining a network of 500+ clinics across higher ed that also use our tools. That peer network is often the source of some of the best ideas for maximizing the value you get out of MedicatOne.

Here’s how the platforms line up on the capabilities campus teams ask about most:

Capacity Medicat Titanium PyraMED Point and Click
Web-based and cloud-hosted Yes No Hybrid Yes
SOC 2 certified security Yes No Yes Yes
Comprehensive student portal Yes No Yes Yes
SIS interfaces supported Yes No Yes Yes
Text message appointment reminders Yes No Yes Yes
Robust built-in reporting tools Yes Limited Limited Yes
Business Intelligence report building Yes No No No
Medical + counseling + immunizations
+ accessibility on one record/platform
Yes No Yes Yes
AI-powered immunization review tool Yes No No No
AI-powered ambient listening tool Yes No No Yes
Custom onboarding and configuration Yes No Yes Yes
Large, experienced & responsive support team Yes Limited Limited Limited
On-site consulting Yes No No No

Competitor data sourced from publicly available sources.

The Bottom Line

If you’re treating student well-being as one connected experience, your technology should too. One modern record, securely hosted, built by a team that has done nothing but serve college health and counseling for three decades, and trusted by campuses of all shapes and sizes. That’s the difference.

We’d love to show you how MedicatOne works. To see our integrated EHR platform in action, reach out to our team.

Industry Articles

Recent Medicat News

Continue reading

EHR Software

How Our Education Resources Maximize Your EHR Value

Buying great software is only the beginning. Research shows that customers who receive post-sale education are 20-30% more likely to adopt a product fully, and 86% say training makes them more likely to stay loyal. At Medicat, we believe your team deserves reliable and thoughtful support long after go-live.

That’s why ongoing training sits at the heart of how we partner with campuses. From articles and product walkthroughs to live sessions with real Medicat experts, we build resources that help your clinic turn features into outcomes.

Why We Invest in Education, Not Just Software

A powerful EHR is only as valuable as your team’s ability to use it. When staff feel confident in a system, they spend less time troubleshooting and more time with students. That confidence does not happen by accident. It’s built through intentional, ongoing education.

Education and training also protect the investment your institution has already made. Unfortunately, turnover is common, and new hires need to get up to speed quickly. Strong educational resources keep knowledge from walking out the door.
 
For campus and clinic leaders, this matters at a strategic level. Better-trained teams mean smoother operations, stronger compliance, and measurable improvements in student care quality.

Self-Paced Learning and Enablement

Every campus works on its own schedule, so we create resources your team can access anytime. These materials meet staff where they are, whether they’re onboarding a new coordinator or exploring an advanced feature for the first time. Our self-paced Help Center is designed to be clear, practical, and easy to search. We focus on real workflows your clinic uses every day, not abstract feature lists.

Resources clinics use regularly include:

  • How-to articles that walk through specific tasks step by step, from patient intake to secure messaging, to immunization compliance tracking.
  • Product walkthroughs that show exactly where to click and why, so staff can follow along in their own environment.
  • Short video tutorials that make it easy to learn a new workflow in minutes rather than hours.
  • Release notes that explain new features in plain language, so nothing gets missed.
  • Webinar recordings that let staff revisit live sessions on demand, whenever it fits their schedule.
  • Biweekly product tip emails enable continued discovery and better efficiency.

Clearly, education doesn’t stop after onboarding at Medicat. It follows our clients through the rhythm of the academic year. Our End of Year Wrap-Up Guide, for example, walks clinic admins through a smooth, stress-free closing each summer, while our Super User Prep Packet gets key staff ready to hit the ground running when the fall semester begins.

These helpful resources ensure our clients feel supported no matter where they are in their Medicat journey. You can explore many of these materials in our Help Center, which we update regularly as our product evolves.

Live Training That Connects People to Answers

Written guides are powerful, but sometimes your team needs a real conversation. That is why we complement our library with live, human-led sessions throughout the year. These sessions give staff space to ask questions, share challenges, and learn from peers on other campuses.

Additionally, our live software trainings include structured onboarding for new clients and role-based sessions to teach specific workflows. We also host refreshers before busy seasons of the year, so your team feels ready when appointment volume spikes.

Live training formats we offer include:

  • Guided onboarding to help new clinics configure and launch with confidence.
  • Role-specific workshops for front-desk staff, clinicians, counselors, and administrators.
  • Seasonal webinars covering topics like immunization season, telehealth trends, and end-of-year reporting tips.
  • Office hours during which clients can bring topic-specific questions and know they’ll walk away with answers.

Support Tickets Provide Another Opportunity for Learning

Not all learning happens from a webinar or a help article. Some of the most valuable teaching moments come from a routine support ticket. That’s because this kind of learning is timely — it happens at the exact moment the client needs it, not weeks later in a training session they may or may not remember.

Our team is trained to “forward resolve” wherever they can, so a simple request doesn’t turn into a second ticket later. Rather than simply fixing the issue, our support agents will walk the person through the fix themselves, so they leave the conversation able to do it on their own next time.

That might mean pausing to explain why a setting works the way it does, or handing back the keyboard so a superuser can enter the change themselves with guidance rather than watching it happen. It’s a small shift, but it adds up. Fewer repeat tickets, more confident clients, and a support relationship that builds capability instead of dependency.

One client put it well: “The support agent was so helpful! She walked me through what I needed to do and had me enter the information myself with minimal guidance so I could learn how to do it on my own. I feel confident I can handle this myself in the future.”

Tailored Value for Every Clinic

Education only works when it speaks to the people using the system. We design our educational resources so each audience finds clear, relevant value.
 
For college health centers, that might mean mastering patient intake, streamlining immunization compliance, or launching telehealth visits. For counseling clinics, it often means smoother scheduling, easier secure messaging, and confident documentation of mental health appointments.
 
For VPSAs and other campus leaders, the payoff is operational. When teams use our college health solutions to their full potential, institutions see better data accuracy, healthier compliance rates, and stronger student outcomes. According to the American College Health Association, well-supported campus health and counseling services play a direct role in student retention and success.

Where We’re Headed Next

We’re proud of how far our education program has come, and we’re not standing still. The next chapter of our roadmap brings more learning directly into MedicatOne itself, so guidance shows up right when and where your team needs it rather than in a separate tab or help article.

We already do this well through our Help Center, live sessions, and everyday support moments, but we see real room to continue growing. Bringing support inside MedicatOne is all in service of the same goal we’ve always had: making confident, capable use of our EHR the natural default for every person on your team.

Key Takeaways

Great software delivers its full value only when the people behind it feel confident and supported. Medicat builds articles, product walkthroughs, videos, and live sessions so your team can turn our tools into better student care. Whether you lead a health center, a counseling clinic, or student affairs as a whole, ongoing education is how you protect your investment and improve student outcomes year after year.

Ready to get more value out of Medicat? Explore our Help Center to see all that’s available to your team today.

Industry Articles

Recent Medicat News

Continue reading

eMar Software

Why More Clinics Should Use eMAR Software

Every year, medication errors harm roughly 1.3 million people in the United States alone, according to the World Health Organization. On a busy campus, a single nurse may administer dozens of doses of medications per day. When that record lives on paper, or even just in a clinical note, the margin for error can grow quickly.

Many college health clinics still track medications by hand, but there are better options available to track doses administered and ensure compliance. Let’s look at how Electronic Medication Administration Record (eMAR) software gives college clinics a safer, simpler way to record medication administration.

One Dose, Fully Documented

It’s easy to think of eMAR as built for the “typical” case: a boarding school student on a daily medication, tracked dose after dose over the course of a semester. But a lot of what a college health clinic administers doesn’t look like that at all: a single dose given during a walk-in visit, a one-time as-needed medication, or even a controlled substance given once and never again.

Those doses are exactly where a transaction code and a typed note fall short, because there’s no ongoing pattern for anyone to compare against later. A guided workflow that confirms the right medication, the right dose, and the right verification step doesn’t just apply to recurring regimens — it’s just as useful, and arguably more protective, the one time it happens. The eMAR doesn’t need a repeat administration to be worth using; it makes that single dose as well-documented and defensible as if it happened every day.

The Problem with Paper Medication Records

Nurse-run clinics or infirmaries often carry a heavy load with a lean team. One or two nurses manage intake, walk-ins, immunizations, and daily medication administration. Paper logs and spreadsheets were never built for that kind of workload.

Manual or paper records create real risks for both students and staff. A rushed entry, a skipped signature, or an unclear dose can slip through unnoticed. And when the same clinic stores controlled substances, the stakes climb even higher.

Common breakdowns in a paper-based clinic include:

  • Missed or double doses when a handoff isn’t documented clearly
  • Illegible or incomplete notes that leave gaps in a student’s health history
  • Inventory blind spots, especially for controlled medications
  • Slow audits, since staff must dig through documents to reconstruct who administered what, and when

These are not small inconveniences. Medication administration is one of the most error-prone steps in the care process, and paper processes offer no safety net when a busy nurse is stretched thin.

How eMAR Software Closes the Gaps

An electronic medication administration record (eMAR) replaces those paper binders with a single, structured system. Instead of hoping a handwritten log is complete, nurses follow a guided workflow that prompts the right action at the right time.

A good eMAR system does more than store data. It actively supports the person giving the dose. The shift from passive record to active guardrail is what makes it so valuable in a nurse-run clinic or infirmary setting.

With Medicat’s eMAR tool, clinics gain features designed for exactly this workflow:

  • A color-coded dashboard that shows upcoming and administered medications
  • Automatic inventory tracking with low-stock alerts, so supplies never run out
  • Double-count verification for controlled substances, adding an extra check
  • Comprehensive audit trails that document who handled each medication, when, and any inventory change

Each of these directly addresses a paper-based risk. The dashboard prevents missed doses on a day-to-day basis, inventory alerts remove the guesswork, and audit trails turn a day-long reconciliation into a quick search.

Safety and Compliance, Built In

Compliance is a constant pressure for campus health leaders. An eMAR system helps by making accurate documentation the default, not an extra task.

Role-based access controls and multi-factor authentication protect sensitive records. Every action is time-stamped and attributed, which means an audit becomes a report you run, not a scramble you dread. For campus leaders weighing operational risk, the value of that reliability is hard to overstate.

Freeing Nurses to Focus on Students

The strongest case for eMAR software is what it gives back: time and attention. When documentation is faster and safer, nurses spend less energy on paperwork and more on care.

Consider a typical morning med pass at a college health clinic. With a paper system, a nurse verifies each student against a printed list, records doses by hand, and later reconciles counts. With an eMAR, the same nurse works from a live dashboard, confirms doses in a few clicks, and the system updates inventory automatically.

That efficiency compounds across a semester. Fewer errors mean fewer follow-ups. Cleaner records mean smoother audits. And a lighter administrative load helps prevent the burnout that strains so many campus health teams.

Because Medicat’s eMAR is part of its broader college health platform, medication data connects to the same record used for intake, immunization compliance, and scheduling. Nurses aren’t toggling between disconnected tools; they work in one place.

Key Takeaways

Paper medication administration records expose college health clinics to avoidable risk. eMAR software closes those gaps with guided workflows, real-time inventory tracking, controlled-substance verification, and complete audit trails.

The result is safer medication administration and more time for the students who count on your team. To see how the right eMAR fits your clinic, explore our interactive eMAR tour.

Industry Articles

Recent Medicat News

Continue reading

immunization compliance tracking

Beating the Spring Immunization Crunch

Immunization compliance has a season. It arrives every spring, when a few clinic staff become responsible for thousands of incoming students who all need to prove, at once, that their compliance status is up to date.

That means staff members spend countless hours manually reviewing PDF documents, cross-checking immunization dates, and chasing down missing forms.

This manual way of managing compliance just doesn’t scale. Automating immunization compliance workflow means moving the whole process into one system. Students upload their records to a portal, the platform pulls what it can from state immunization registries, and AI tools verify the documentation against what the student entered. Staff only touch the records that actually need a human eye.

Why Manual Immunization Review Breaks Down at Scale

Most compliance backlogs aren’t caused by students refusing to comply. They’re caused by the tedious nature of document review. Records arrive as photos, faxed forms, patient portal printouts, and emailed attachments, each in a different layout. A staff member has to open each one, find the right vaccine, confirm the date and dosages, and mark the student as compliant.

Alternatively, if any issues are found with the student’s submitted documentation, staff spends additional time marking the records as non-compliant and following up individually with the student via email, phone call, or sending reminders in the mail.

Multiply that by an incoming class between a couple hundred and multiple thousands of students, and the math gets ugly fast. Reviews pile up, registration holds linger, and your staff field a steady stream of (sometimes frustrated) “am I cleared yet?” calls during the busiest stretch of the year.

The Four Pieces of an Automated Compliance Workflow

A modern immunization compliance workflow leans on a handful of connected tools rather than one magic button:

  • A student-facing portal where incoming students upload documents and complete electronic forms in one place; no emailed PHI, no papers to scan into the EHR.
  • State registry integrations that automatically pull records for students vaccinated in-state. Medicat maintains interfaces with the immunization registry in nearly every state.
  • A nationwide retrieval option (VeriVax) so out-of-state students can pull their records through a vast clinical network instead of hunting for a paper copy from their pediatrician.
  • ICM Agent uses AI to read any uploaded documentation and approve or flag each compliance requirement as verified or unverified.

What Changes for Your Staff

The goal isn’t to remove people from the immunization compliance process. The goal is to point staff towards the submitted documents that most need human review. Your team stops being data-entry clerks and starts being reviewers, stepping in on the exceptions (an unusual record or an exemption request) rather than every single file submitted by your students.

Plus, automated reminders nudge students about missing items, and real-time compliance status lets students see exactly what they still owe without calling anyone. Institutions using all of these tools together report spending far less time on compliance each summer.

Getting Started Before the Next Enrollment Cycle

The practical move is to have the automated workflow live before your next wave of incoming students, not during it. MedicatOne ICM implementations can go live in as little as one month, which means that we can work with your clinic’s schedule to implement tools like Verivax and ICM Agent.

If you’re evaluating options, ask how each vendor handles the three challenging aspects of immunization compliance on campus: in-state records, out-of-state records, and international student records. A system that has an answer for all three is one that will actually reduce your backlog instead of just relocating it.

To see our compliance tools in action, request a live walkthrough with our team.

Frequently Asked Questions

  1. Can immunization tracking really be automated for a large incoming class?
    • Yes: registry integrations, nationwide record retrieval, and AI-assisted verification are built to handle thousands of records at once. This allows campuses to cut time spent on immunization compliance by up to 90%, even during peak intake periods.
  2. What happens to records that don’t match the data a student has entered?
    • They’re flagged as unverified for staff to review. The system clears the straightforward cases automatically and routes only the genuine exceptions to a person, so no questionable compliance documentation is auto-approved.
  3. How quickly can these tools be in place at my school?
    • Medicat implementations can go live in as little as one month, but often take between 8 and 12 weeks, depending on the size and complexity of your clinic and student body.

Industry Articles

Recent Medicat News

Continue reading

Students Immunization Records

Can Students Upload Their Own Immunization Records Online?

A common way students still submit immunization records (email) is also one of the least secure.

That’s why it’s so important that students can now upload their own immunization records online through a secure student portal and then track their compliance status in real time. Then MedicatOne handles much of the verification behind the scenes, giving students a clear answer on what they still need to submit.

This self-service model has quickly become the norm in college health, for good reason: it’s faster for students and less of a burden for the clinic.

How the Upload Process Works

A student logs into the portal, uploads a photo or PDF of their records, and enters the corresponding vaccine dates into a structured form. Keeping both the document and the entered data in one place is what makes automated verification possible later.

Just as important is what the student portal replaces. Emailing immunization records is a HIPAA problem, and faxed or paper forms create scanning work for staff. A centralized, easy-to-access online portal removes both.

Where the “Verify” Part Comes In

Students don’t verify their records in the sense of self-certifying and being done. Instead, the platform does the checking. Medicat’s ICM Agent compares the documentation the student uploaded against the dates they entered and marks each immunization as verified or unverified. Your staff remains in control of final verification status and can manually mark any student as compliant or non-compliant, if needed.

For students who were vaccinated in-state, records can often be pulled directly from the state immunization registry. Out-of-state students can retrieve their records through VeriVax, a nationwide clinical network of immunization registries. The result is that verification happens with far less manual back-and-forth and effort from both the student and your staff.

Real-Time Status Keeps Students Moving

The feature students notice most is status visibility. Rather than guessing whether they’re cleared, they see their compliance status update as various requirements are processed:

  • A clear list of what requirements are complete and what’s still outstanding
  • Automated reminders for missing items, so nothing slips before a registration hold hits
  • One place to resubmit if something didn’t match (no phone tag with the front desk!)

Does Self-Service Mean Less Accurate Records?

No: self-service compliance does not mean just taking a student’s word for it. That’s why the documentation and detailed immunization data are compared rather than trusted at face value. And of course, staff can still review and override any status decision made by our compliance tools.

Students do the uploading (or VeriVax does it for them), our system does the review, and your team steps in only where a record genuinely needs a human to take a look. That division of labor is what makes online upload both easier and more reliable than the paper process it replaces.

The Payoff for Your Clinic

When students handle their own uploads and can see their status, the volume of “where do I stand?” calls drop sharply. This frees up front-desk staff during the exact weeks they’re most stretched thin. Combined with automated verification, institutions report spending significantly less time verifying immunizations.

Frequently Asked Questions

  1. Is it safe for students to upload health records online?
    • Yes: when it’s done through a secure student portal rather than email. A portal keeps immunization documents in a protected, access-controlled environment. This avoids the HIPAA risks of emailing or faxing records.
  2. Do students self-certify, or is the record actually verified?
    • The record is verified either by technology, or manually by your staff.
  3. What if a student was vaccinated in another state?
    • Out-of-state students can retrieve their records through VeriVax, a nationwide clinical network of immunization registries. This eliminates the need to track down a paper copy from a previous provider to then email, fax, or mail the record to their school’s health center.

Key Takeaways

Online immunization record upload turns a paper-heavy chore into a self-service workflow students can finish in minutes. Students upload and enter their records, automated verification does the first pass checking through tools like ICM Agent and VeriVax, and your staff step in only when a record genuinely needs a human.

The result is faster compliance for students, fewer calls and emails fielded by your front desk team, and records that are more accurate than the paper process they replace.

See how MedicatOne streamlines immunization compliance for your campus clinic.

Industry Articles

Recent Medicat News

Continue reading

User Permissions within EHR Software

Why User Permissions Matter Within EHR Software

Since 2009, more than one billion healthcare records have been exposed in U.S. data breaches. On a busy college campus, dozens of people may touch a single student’s health record, front-desk staff, nurses, counselors, and student workers alike. User permissions decide who sees what, and that decision protects your students, your staff, and your clinic.

What User Permissions Actually Do

User permissions are the rules that control access inside your EHR software. They set what each staff member can view, edit, or share. Think of them as digital keys, cut to fit each person’s job.

A medical assistant may need to check in patients and update vitals. A counselor needs to view counseling notes, but not immunization records. Clear access rules make sure each person only reaches the tools and information their role requires.

This approach is often called role-based access control. Instead of managing access individually for each user, you assign a “permission group,” and the role carries the right permissions. It keeps setup simple and consistent as your team grows.

Protecting Student Privacy and Staying Compliant

College health and counseling records are sensitive by nature. Students share details about mental health, sexual health, and chronic conditions. They trust that this information stays private

Well-designed user permissions support that sense of trust directly. They limit access to the people who truly need it, which is the heart of the HIPAA minimum necessary standard. Fewer eyes on a record means fewer chances for a breach.

Permissions also help you maintain any necessary separation between medical and counseling records. Many campuses keep therapy notes separate from primary care files. Your EHR should allow for the flexibility necessary to protect counseling notes while still coordinating care across clinics when appropriate.

For VPSAs, this is more than a technical detail. A single privacy incident can damage student confidence and invite regulatory scrutiny. Thoughtful access controls lower that risk across the whole division. You can read more about how EHRs safeguard student privacy.

Fewer Errors and Cleaner Workflows

Access rules do not only guard privacy. They also make daily work smoother and more accurate. When staff see only the screens they use, the EHR system feels less cluttered.

Consider a few everyday examples on campus:

  • A student worker checks in patients but cannot open sensitive clinical notes.
  • A front-desk clerk schedules appointments without editing diagnoses.
  • A billing specialist views CPT codes without changing other chart data.
  • A counselor documents sessions without touching medical prescriptions.

Each of these guardrails prevents an accidental edit in the wrong place. That means fewer corrections later and cleaner records overall. Good permission settings quietly reduce the small mistakes that add up over a semester.

Supporting Accountability and Audits

Higher education clinics face regular reviews from auditors and leadership. You may need to show exactly who accessed a record and when. User permissions, paired with audit logs, make that easy to prove.

Because each person signs in under their own account, activity ties back to a real user. If a question arises, you can trace the history with confidence. This transparency protects both students and the staff doing the work.

Clear roles also simplify onboarding and offboarding. When a new nurse joins your clinic, you can assign them a specific set of permissions to ensure they’re accessing the right areas of the EHR platform.

MedicatOne also has group-based permissions, which allow you to define permissions for groups like “Compliance Specialist,” or “Triage Nurse,” or “Front Desk” that have a stock set of permissions. Then you can still customize at the individual level as needed. These are just some of the permission-focused features that clinic leaders value most.

Building Permissions That Fit Your Campus

Every campus health and counseling clinic operates uniquely. Your permission structure should reflect how your teams actually work together. Start by mapping each role to the tasks it truly performs. Here are a few practical steps to guide the process:

  1. List every role in your clinic, from providers to student staff.
  2. Match each role to the minimum access it needs to do the job.
  3. Review permissions at the start of each semester, since roles, responsibilities, and staff change often.
  4. Compare settings across medical and counseling teams based on your clinic’s integration philosophy and policies.

Key Takeaways

User permissions are a quiet but powerful part of any campus EHR software. They protect student privacy, support HIPAA compliance, reduce errors, and make audits far less stressful. For clinic leaders and VPSAs, they turn a complex system into one that is safe and easy to manage.

To see how flexible, role-based access can work on your campus, schedule time to meet with our team.

Industry Articles

Recent Medicat News

Continue reading

Medicat’s Product Updates

Thoughtful by Design: Medicat’s Approach to Product Updates

By Ann Wright, Chief Product & Technology Officer at Medicat

Many software companies measure themselves by how many new features they ship. I’ve come to believe that’s the wrong scoreboard for campus wellness. A product release can have a big impact on clinic operations if it’s not thoughtfully executed. Thus, these changes warrant careful consideration.

Medicat’s approach to change starts from an unglamorous premise: more is not better. Better is better. And better for college health and counseling clinics has everything to do with when and how.

More Releases Don’t Necessarily Mean More Progress

It’s tempting to treat release velocity as proof of momentum. But every change carries risk, and that risk doesn’t land just on us; it lands on a counselor between sessions or a nurse mid-intake.

A feature that looks clean in a beta environment may behave differently during the rush of the early fall semester. This is where trust is won or lost. We prefer to ship changes we feel confident about, even if the number is smaller, instead of a stream of updates that keep your team guessing.

It’s always top of mind that our software helps real clinics run on college campuses. And they need our product to work reliably.

We Time Releases to the Academic Calendar

Campus health and counseling clinics don’t operate on a standard corporate calendar. They run on move-in, immunization compliance season, midterms, and the counseling surge that follows every break. Our release schedule follows that rhythm.

The heavy lifting happens when your clinic can absorb it:

  • Summer and lower-traffic windows for larger platform updates, so new capability arrives before the students do.
  • Quiet periods for anything that changes a core workflow like patient intake or scheduling.
  • Minimal change during peak load, when a stable system matters more than a new one.

We built MedicatOne to serve medical and counseling teams on the same platform. Coordinating releases to work with, rather than fight against, the academic year, is how we keep that shared system dependable when clinic demand spikes.

Predictable Beats Fast

Here’s a small change we’ve made that carries a lot of weight: we exclusively ship major releases on Saturdays instead of midweek.

Throughout our years of experience working with campus health, we’ve learned that a change that goes live on a Wednesday can surprise a clinic in the middle of its busiest stretch, with no time to adjust. A Saturday release lands when clinic traffic is at its lowest, and it gives teams extra runway before clinic doors open on Monday.

Predictability is a feature. When you know a release is coming and what it will include, you can plan for it (instead of reacting to it).

Campus health and counseling teams are already stretched thin. The last thing an overextended team needs is an unannounced change to the tool they rely on. So, we plan our product release schedule deliberately and with care to ensure minimal disruptions for clinicians and staff.

At Medicat, quality control is a cross-team effort that builds upon the work of our dedicated quality assurance team. Company-wide “bug bashing” occurs in the weeks leading up to a release. Clients with sandboxes receive a sneak peak, which allows them to test features in the wild with their real workflows, alongside someone from our Customer Success team.

Additionally, we host a webinar before every product release to help our customers understand each change. These events are an open invitation for anyone to question why or how we’re releasing a certain feature before it goes out.

Communication Is Part of the Release

A release is more than just deploying new code to our software. It also includes proactive communication to our clients to help them understand why the updates we’re making will be beneficial to their workflow. This communication begins weeks before the actual product release date.

Before any new features or tools ship, we tell our clients what’s changing, why, and what to expect. We give Super Users and clinic directors the context to prepare their teams, and we leave room for questions via email communications and webinar events before a release, rather than after.

Our goal with all pre- and post-release communications is to ensure we deliver changes in a way that teams can absorb easily and quickly implement into their workflows.

Key Takeaways

Our product release philosophy comes down to discipline over spectacle: ship fewer, better-tested changes; time them to the academic calendar; avoid mid-week surprises; and communicate proactively before each product release.

The goal isn’t to impress you with how often we release new features. It’s to make sure the system holds when your campus needs it most.

If that approach resonates, explore how we think about dependable campus health and counseling EHR technology in our resource center, or request a demo to see how MedicatOne can support your team.


About the Author: Ann Wright is the Chief Product & Technology Officer at Medicat, the electronic health record platform built specifically for college and university health and counseling centers. She leads product and engineering with a focus on the unglamorous work that matters most in campus health: reliability, integration, and systems that hold up under the real pressures of a semester. Her guiding belief is that the burden of complexity should land on the software, not on clinical teams.

Industry Articles

Recent Medicat News

Continue reading

Clinic integration

Your Clinic Can Be ‘Integrated’ and Still Not Work Together

Insights from Medicat’s Chief Customer Officer, Amy Smith

Right before the American College Health Association Annual Conference, Medicat hosted a session in Denver with health and counseling leaders from campuses across the country. One line kept coming back, phrased differently by different people, but always the same idea underneath: health and counseling clinics can be “integrated” on paper and still not function as one team.

That gap is worth unpacking: what it means, where campuses actually stand today, and what it takes to close it.

What our clients told us

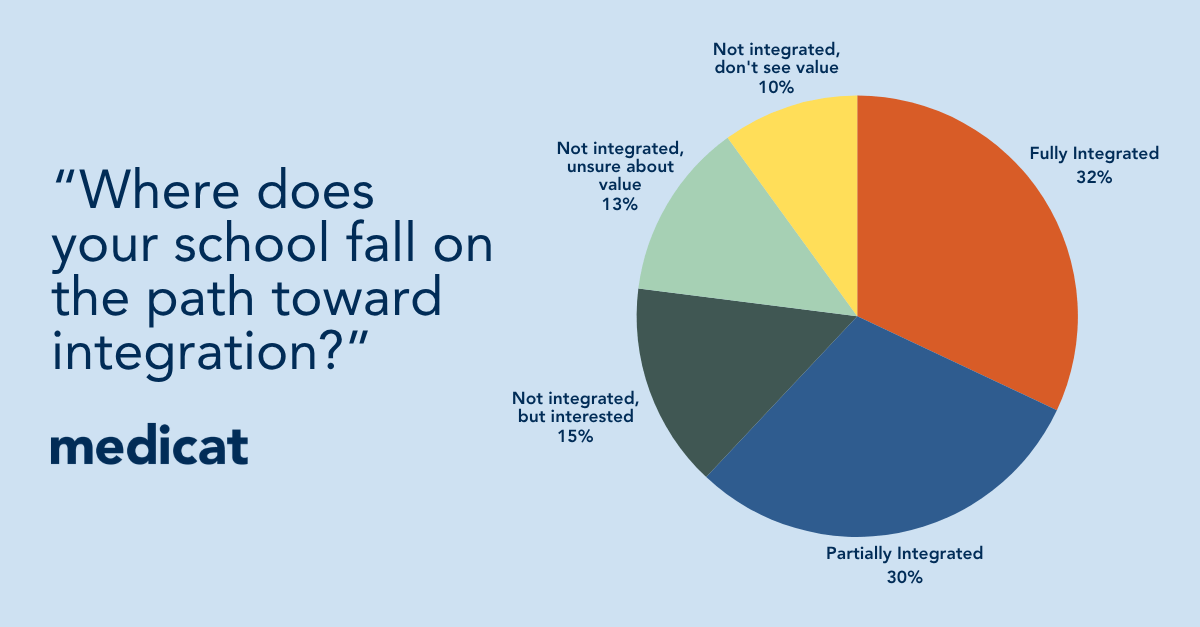
We asked our clients a simple question: Where does your school fall on the path toward integration? The topline: 62% are integrated or actively working toward it. That splits into 32% fully integrated today and 30% partially integrated and actively moving toward it.

The remaining 38% aren’t there yet, and they don’t all look alike: 15% are not integrated but interested. 13% are not integrated and unsure about the value. 10% are not integrated and don’t see the value.

Clinic Integration Infographic

A few things stand out once you sit with that data. Integrated care, once an edge case, is now the majority experience. Any conversation about the future of campus health and counseling should start from the assumption that most schools are already moving in this direction.

We imagine the 15% who are interested and exploring if integration is worth doing are looking for a clear, low-risk path: how do you sequence the work, what does the data infrastructure need to look like, and what have peer schools learned along the way? For some schools, they may be constrained by bandwidth. Others may be concerned about autonomy.

Counseling teams in particular are often concerned about protecting the confidentiality of sensitive conversations. Done well, integration should answer that concern rather than override it — with explicit, agreed rules about what moves between medical and counseling records and what stays sealed. For other schools, implementing an integrated and collaborative model may raise legitimate questions about staff time before the integration pays off.

What “integrated” truly means

It’s tempting to treat integration as a binary. A school either is embracing integrated care, or it isn’t. But the room in Denver made something clear: two schools can claim integration and be describing completely different realities.

For one school, “integrated” might mean medical and counseling are co-located physically or connected electronically, and not much else. For another, it means more deliberate collaboration — shared records, shared treatment planning, warm handoffs, a care team working from a single picture of the student.

Same word. Different worlds.

National research backs up what we heard from clients: co-location is real, and it’s growing. But it isn’t the same thing as collaborative care, and having providers under one roof doesn’t automatically produce collaboration. It’s entirely possible to merge two departments, put them in the same building, and still end up with two parallel operations — different EHR systems, different treatment philosophies, referrals that go out but don’t come back with any real follow-up.

There’s a useful way to think about why: structure is the skeleton of integration — org chart, shared records, financial model, the workflows that dictate what happens when a student needs both sides of care. Relationship is the muscle — it’s what actually moves things day to day, but muscle can’t hold a shape on its own. The skeleton is also required.

A school can have great relationships between clinic leaders and still fail at integration if there’s no defined process for a warm handoff, no shared record forcing visibility, no accountability for what happens after a referral goes out. Relationship without structure is fragile: it depends on a couple of people who happen to work well together, and it collapses the moment either of them leaves.

So when we ask a campus “where are you on integration?” the real follow-up is integrated in what sense? A school that reports being “fully integrated” because medical and counseling report to the same director, share a building, and use one EHR may be in a completely different place than a school that’s integrated on the org chart but still running two disconnected workflows underneath. Integrated, yes. But not necessarily delivering collaborative care.

The bigger picture

The same tension shows up in the national conversation, too. Behavioral health integration into primary care has been described by leaders in the field as one of the most significant growth areas in psychology and primary care generally, with a striking gap still in place. A large share of primary care providers nationally still don’t have a behavioral health professional on their care team at all, even as awareness of the model’s benefits has expanded.

Integration is increasingly understood not as a nice-to-have, but as one of the more promising responses to our nationwide capacity problem: catching concerns earlier, in the medical visit, before they become a mental health crisis.

National data on colocation also confirms what our clients are telling us: physical colocation of medical and behavioral health providers is expanding, but it’s happening unevenly. It’s much more common in larger, urban, better-resourced settings, and still rare in smaller or rural practices, which are often the ones that could benefit from it most.

That maps almost exactly onto the segment of our own survey respondents that selected “not integrated, unsure about the value.” It’s worth asking whether resourcing, not philosophy, is the real barrier for a meaningful share of that group. If it is, the answer isn’t a harder pitch on the value of integration — it’s a lower-cost, lower-lift path into it. That reframes the “unsure” group almost entirely: not skeptics who need convincing, but under-resourced teams still looking for a way in.

Where this leaves us

As we think about how to support the schools moving through this journey, the more precise question to ask isn’t just “are you integrated?” It’s “do your providers share a record, share a plan, and actually collaborate about the student in front of them?”

That’s the standard worth building toward, and it’s the standard we want our platform to make easier to achieve, not just easier to claim.

If you would like some consultation on starting the journey toward collaborative care, please reach out. We can talk about Medicat as a platform built for integrated health and connect you with the schools already thriving within a collaborative model.

FYI: This data is based on a recent Medicat client survey (n=238) and conversations with client health and counseling leaders during the 2026 ACHA Annual Meeting in Denver, Colorado.


About the Author: Amy Smith is the Chief Customer Officer at Medicat, the electronic health record platform purpose-built for university health and counseling centers. She leads the teams responsible for customer success, support, and partnership, and serves as the internal advocate for the directors and clinical staff who run campus health centers every day. Her work is grounded in real conversations with those teams: what they carry, what they need, and what too often goes unrecognized.

Industry Articles

Recent Medicat News

Continue reading